The Centers for Medicare & Medicaid Services (CMS) has issued its updated National Coverage Determination (NCD) for transcatheter aortic valve replacement (TAVR), concluding a nine-month review process that included extensive engagement from The Society of Thoracic Surgeons (STS) and partner organizations representing the multidisciplinary heart team, including the American College of Cardiology (ACC), the Society for Cardiovascular Angiography & Interventions (SCAI), and the American Association for Thoracic Surgery (AATS).
The final NCD follows CMS' June 15, 2026, proposed decision to update the existing TAVR coverage policy. Throughout the review, STS provided extensive feedback and advocated for policies that preserve the multidisciplinary heart team model, maintain appropriate cardiac surgeon involvement in TAVR evaluation and care, and support continued evidence development as TAVR expands into additional patient populations and indications. View a comparison chart of the existing NCD, proposed changes, and final policy.
STS Advocacy Throughout the Process
STS was actively engaged throughout the NCD review, working both independently and as part of a multi-society coalition. The Society submitted formal comments, met with CMS officials involved in developing the policy, engaged CMS leadership, and participated in discussions with the NCD requester Edwards Lifesciences and other professional societies regarding areas of potential consensus.
Throughout the process, STS consistently advocated for three priorities:
Preserving the multidisciplinary heart team model as an essential component of TAVR decision-making.
Maintaining cardiac surgeon involvement in patient evaluation, treatment decisions, and TAVR care.
Continuing evidence development in areas where important clinical questions remain unanswered.
STS also advocated for expanded evidence development requirements as TAVR moves into newer indications and lower-risk patient populations, including severe bicuspid aortic stenosis, moderate aortic stenosis, pure aortic regurgitation, valve-in-valve procedures, and patients at low surgical risk.
From the Existing Policy to the Final NCD
The original TAVR NCD, established in 2012, helped guide the measured adoption of TAVR in the United States by establishing coverage requirements that included participation by a multidisciplinary heart team and the availability of on-site cardiac surgical services.
CMS reopened the NCD in December 2025 following a request from Edwards Lifesciences. During the subsequent review, STS worked to ensure that an updated policy would recognize advances in TAVR while maintaining safeguards that support patient safety, multidisciplinary decision-making, and evidence-based care.
CMS released its final NCD on September 10, 2026. The NCD maintains requirements for hospitals to have on-site cardiac surgery capabilities and access to critical care resources and continues to recognize the multidisciplinary heart team. CMS removed coverage with evidence development (CED) status for severe symptomatic aortic stenosis (AS). It has approved TAVR for asymptomatic severe aortic stenosis but under the provision of CED.
CMS defined the heart team as at least one cardiologist and one surgeon, but also included advanced practice providers, nurses, and other members. While the suitability for surgical aortic valve replacement must be evaluated, the only mandated in-person visit is the TAVR operator. They state that another evaluation by an additional heart team TAVR operator is not required but is covered if performed. A single TAVR operator is acceptable, and it may be a cardiologist or surgeon. If determined appropriate by the heart team, a second operator would be supported and it may be a cardiologist or a surgeon.
What the Final NCD Means
The final policy maintains several important elements of the existing TAVR coverage framework, including:
Continued requirements for hospitals to have on-site cardiac surgery capabilities.
Continued access to critical care resources.
Recognition of the multidisciplinary heart team.
Coverage with evidence development for asymptomatic aortic stenosis.
Looking Ahead
STS will continue to monitor implementation of the final NCD and advocate for evidence-based TAVR care, patient safety, outcomes, and policies that support multidisciplinary decision-making, appropriate surgical expertise, and rigorous evidence development.
Summary: The final NCD maintains key elements of the existing TAVR coverage framework, including hospital requirements for on-site cardiac surgery capabilities and critical care resources, continued recognition of the multidisciplinary heart team, and CED for asymptomatic aortic stenosis. While the policy does not incorporate all of STS' recommendations regarding cardiac surgeon involvement and expanded evidence development, STS will continue working to ensure that patient safety, multidisciplinary care, and high-quality clinical evidence remain central to TAVR treatment and coverage decisions.
Our work does not end with the CMS announcement. This is an opportunity for every surgeon involved in valve therapies to stay actively engaged in your heart team, make every effort to evaluate all patients being considered for TAVR or SAVR, and apply all available evidence to provide informed decisions that protect patients. STS will continue to advocate for evidence-based policies that support multidisciplinary care, appropriate surgical expertise and the highest-quality care for patients with structural heart disease.
For Sean Jordan, MD, the need was clear: Too many patients across East Tennessee faced significant barriers to lung cancer screening—not because they lacked the need for screening, but because they lacked access to it.
East Tennessee has some of the highest smoking and lung cancer rates in the country, while screening rates remain below national averages. For patients in rural Appalachian communities, mountain roads, long travel distances, limited specialty care, and a lack of CT scanners in many counties can make screening especially difficult.
Image
Dr. Jordan is the co-director of thoracic oncology at UTMC.
Jordan, chief of thoracic surgery and director of lung cancer screening at the University of Tennessee Medical Center (UTMC), saw an opportunity to bring screening directly to the communities that needed it most.
The result is a 45-foot mobile CT lung cancer screening unit designed to serve patients across 21 counties in East Tennessee.
“We needed something that could navigate our geography and be convenient and inviting for patients,” Jordan said.
Making the Mobile Unit a Reality
Bringing the vision to reality required more than clinical expertise. It required funding, collaboration, persistence, and advocacy.
The University of Tennessee Medical Center already had a robust lung cancer screening program, but funding a mobile program presented a significant challenge. Working with Congressman Tim Burchett, the team secured $2.3 million through the U.S. Department of Agriculture to fund the mobile unit and supporting software.
The team then pursued a competitive Rural Health Resiliency grant through the Tennessee Department of Health to support program personnel. STS Advocacy strengthened the application by providing a letter of support from then-STS President Dr. Jenna Romano.
The effort ultimately resulted in a $5.45 million grant—one of the largest awarded in the state—to support personnel for the mobile lung cancer screening program and a mobile mammography program.
Jordan also credits Rob Headrick, MD, chief of thoracic surgery at CommonSpirit-Memorial Hospital-Rees Skillern Cancer Institute-Chattanooga and chair of the STS Workforce on Health Policy, Reform, and Advocacy, with providing guidance and connecting the team with STS Advocacy resources.
Bringing Screening to Patients
The mobile unit will bring CT screening and a multidisciplinary team—including technologists, nurses, patient liaisons, and behavioral health professionals—directly into underserved communities.
“Many patients are not willing to travel outside their communities to seek even basic care,” Jordan said. “We can bring our medical expertise and the CT scanner itself directly to their communities.”
The program will also provide tobacco cessation services, education, and centralized coordination to help patients who need additional care move through the health care system more quickly.
Ultimately, success will be measured by whether more cases of lung cancer are detected at an earlier, more treatable stage.
A medical oncologist once told him that fewer patients seemed to be arriving with stage II and III lung cancer. “That to me is the biggest win I can think of for this community,” Jordan said. “We are shifting the stage of lung cancer earlier to when it is most survivable.”
Leading Through Advocacy
The project took two years to move from funding to implementation, but Jordan hopes its impact extends beyond East Tennessee.
“Reaching out to other mobile lung programs and STS Advocacy can introduce you to a community of like-minded groups” who can share their experiences and help develop programs that work for individual communities, he said.
The experience reinforced Jordan's belief that thoracic surgeons should play a leading role in strengthening screening programs nationwide.
“Apart from patients and families, no one in the hospital sees the benefits of a robust lung cancer screening program as much as thoracic surgeons,” he said. “We should be leaders and advocates for strengthening our own programs and all programs nationwide.”
Over the past 25 years, Medicare physician reimbursement has fallen by approximately 33% after adjusting for inflation, even as the cost of delivering care has continued to rise. This widening gap threatens patient access to care, places increasing financial pressure on physician practices, and undermines the long-term sustainability of the physician workforce.
Host Dr. Melanie Edwards is joined by guest Dr. Andrea Wolf, director of the New York Mesothelioma Program, professor of thoracic surgery at the Icahn School of Medicine at Mount Sinai, chair of the American Association for Thoracic Surgery Wellness Committee, and an accomplished marathoner. Dr. Wolf explores how the mindset and discipline of distance running can strengthen resilience, performance, and career longevity in surgery.
Justine Varieur Turco has been appointed Chief Executive Officer/Executive Director effective Aug. 31, 2026. Turco brings more than 20 years of executive leadership experience in medical publishing, education, and professional societal leadership.
Latest Impact Factor places the journal first in the specialty and in the 95th percentile of surgery journals overall.
The Annals of Thoracic Surgery is now ranked first among cardiothoracic surgery journals based on the latest Journal Impact Factor. The ranking also places the journal in the 95th percentile of surgery journals overall and is the highest Impact Factor in its history.
The Journal Impact Factor is a widely used measure of how frequently on average articles published in a journal are cited by other researchers within two years of publication. It is among the most widely recognized of several indicators used to assess a journal's influence.
"It's a key milestone for the journal," said Editor-in-Chief Joanna Chikwe, MD, chair of the Department of Cardiac Surgery in the Smidt Heart Institute at Cedars-Sinai Medical Center. "For many years, The Annals has been the primary journal cardiothoracic surgeons tend to read and submit their work to. So, seeing it ranked first in the specialty is a great reflection of the quality of that work and the care that goes into the review process."
The editorial team receives more than 3,000 manuscript submissions each year. Fewer than 10% of original research articles are accepted for publication in The Annals, with approximately 15 to 20 appearing in each monthly issue following editorial assessment and scientific peer review. Dr. Chikwe said the ranking reflects the contributions of the journal's international community of authors, reviewers, and editorial board members.
"Peer review depends on people giving their time and expertise," she said. "Our reviewers help strengthen the science, our editorial board provides thoughtful guidance, and our authors choose The Annals for some of their most important work. This recognition belongs to that community of volunteers who make the journal possible while balancing busy clinical and academic careers."
The journal has also launched the Annals Peer Reviewer Academy, a mentorship program designed to train early-career cardiothoracic surgeons in scientific peer review. The inaugural program received over 45 applications for ~10 available spots.
In 2025, articles published in The Annals of Thoracic Surgery during the previous four years received approximately 13,000 citations. Based on those citation metrics, the journal also ranked ahead of leading journals, including JAMA Surgery.
"We'll continue to focus on publishing compelling research, guidelines, clinical cases and reviews across adult cardiac, thoracic, and congenital heart surgery," Dr. Chikwe said. " Our north star is contributing to better patient care, in a landscape that science and technology are transforming."
Top 10 Cited Articles from The Annals of Thoracic Surgery in 2025
Top 10 Cited Articles from The Annals of Thoracic Surgery
Rank
Article Title
Citations
Year
Vol (Issue)
1
EACTS/STS Guidelines for Diagnosing and Treating Acute and Chronic Syndromes of the Aortic Organ
103
2024
118 (1)
2
Perioperative Care in Cardiac Surgery: A Joint Consensus Statement by the Enhanced Recovery After Surgery (ERAS) Cardiac Society, ERAS International Society, and The Society of Thoracic Surgeons (STS)
90
2024
117 (4)
3
The Society of Thoracic Surgeons Intermacs 2023 Annual Report: Focus on Magnetically Levitated Devices
72
2023
117 (1)
4
The Society of Thoracic Surgeons Adult Cardiac Surgery Database: 2022 Update on Outcomes and Research
53
2023
115 (3)
5
The Society of Thoracic Surgeons Intermacs 2022 Annual Report: Focus on the 2018 Heart Transplant Allocation System
51
2023
115 (2)
6
Cardiac Surgery After Transcatheter Aortic Valve Replacement: Trends and Outcomes
48
2024
118 (1)
7
The Society of Thoracic Surgeons 2023 Clinical Practice Guidelines for the Surgical Treatment of Atrial Fibrillation
40
2024
118 (2)
8
Survival After Surgical Aortic Valve Replacement in Low-Risk Patients: A Contemporary Trial Benchmark
37
2023
117 (1)
9
Multiarterial vs Single-Arterial Coronary Surgery: 10-Year Follow-up of 1 Million Patients
32
2024
117 (4)
10
The Society of Thoracic Surgeons Intermacs 2024 Annual Report: Focus on Outcomes in Younger Patients
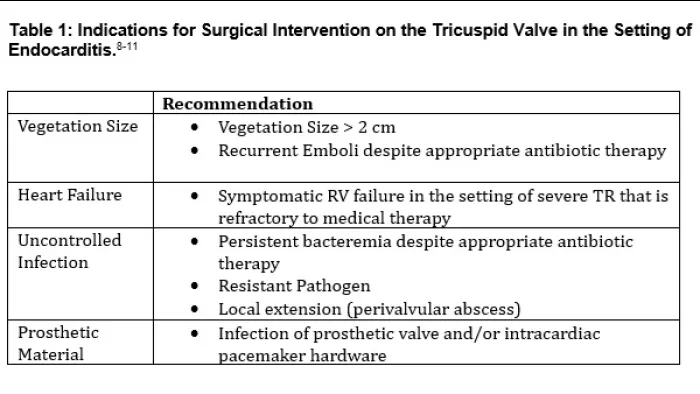
The ongoing opioid crisis has led to a marked increase in tricuspid valve endocarditis (TVE), particularly among people who inject drugs (PWID). This trend presents cardiac surgeons with complex clinical and psychosocial challenges, as patients often face overlapping issues—including infection, addiction, and social instability. These factors complicate surgical decision-making and underscore the need for comprehensive, multidisciplinary approaches to care.
To address the lack of clear surgical guidance and the unique challenges associated with TVE in PWID, the Society of Thoracic Surgeons (STS) convened a multidisciplinary panel to develop expert consensus statements focused on clinical decision-making in this high-risk population.
“Unlike left-sided endocarditis, TVE lacks definitive data to guide surgical timing and intervention strategies,” said Joshua Goldberg, MD, of Weill Cornell Medicine, who chaired the task force that produced the document. “This consensus document represents an important step forward, organizing expert recommendations into key categories that reflect the multifaceted clinical challenges encountered in managing PWID with TVE. Each group of statements addresses specific, real-world dilemmas faced by the multidisciplinary care team.”
The eight core categories outlined in the document include:
Vegetation size
Influence of microbial organism on surgical decisions
Management of persistent bacteremia and timing of antibiotics
Prosthetic valve infection
Decisions around valve removal, repair, or replacement
Prosthetic type selection
Use of emerging technologies such as transcatheter debulking
Ethical challenges of recurrent disease in the context of substance use
A Thorough, Multidisciplinary Approach to Consensus Building
The STS writing group employed a rigorous, evidence-based methodology to develop the consensus statements, incorporating a comprehensive literature review and a modified Delphi process. The evidence review was guided by PICO Framework (Patients/Population, Intervention, Comparison/Control, Outcome)-formatted questions, ensuring a structured and focused appraisal of the data. Consensus statements were established in the first round of voting, with a minimum threshold of 75% agreement required from a multidisciplinary panel that included cardiac surgeons and infectious disease specialists
Navigating Complex Decisions in Endocarditis
“First, surgeons and treatment teams must always remember that tricuspid endocarditis in the setting of injection drug use is a symptom and sign of the disease of addiction. Effective care requires addressing both the infection and the underlying pathology of addiction,” said Dr. Goldberg. “Second, published surgical indications for tricuspid valve surgery are largely extrapolated from data derived from studies on left-sided valve disease. When combined with complex psychosocial factors, the decision to operate can be enigmatic and is best approached through thoughtful, multidisciplinary evaluation.”
A Practical Framework for Attentive, Evidence-Informed Care
Ultimately, this expert consensus provides cardiac surgeons with a practical, evidence-informed framework for managing TVE in PWID. It supports individualized decision-making while promoting standardization in key areas such as vegetation assessment and the use of emerging technologies. Most importantly, it emphasizes the need for compassionate, team-based care that integrates medical, surgical, and psychosocial perspectives. The document serves not only as a clinical tool, but also as a call to action—to treat not just the infection, but the patient as a whole.
In addition to offering clinical guidance, the consensus highlights critical knowledge gaps that demand further investigation. “Because published surgical indications are largely extrapolated from studies on left-sided valve disease, the true indications and optimal timing for intervention remain unclear—particularly in the absence of uncontrolled sepsis or right heart failure,” Dr. Goldberg noted. “We also lack a clear understanding of the efficacy and utility of transcatheter therapies, which have seen a dramatic rise in use in recent years.”
“The Society of Thoracic Surgeons applauds the House bipartisan Doctors Caucuses for their leadership in developing the Patients First Act,” said STS President Vinay Badhwar, MD. “STS has worked closely with members of the caucuses throughout this process, and we are encouraged to see several longstanding physician priorities reflected in the legislation.
In particular, we appreciate the inclusion of meaningful reforms to Medicare's budget neutrality policies and provisions based on the Access to Claims Data Act—legislation developed with strong input from STS to improve physicians' access to timely, comprehensive Medicare claims data.
These policies represent important steps toward a more stable and transparent Medicare payment system that better supports physicians and the delivery of high-quality patient care. We look forward to continuing to work with Congress to advance these reforms and strengthen the Medicare program for both patients and physicians."
The Best Science Presented at the 2026 American Society of Clinical Oncology Annual Meeting
The STS 2026 Best of Lung Cancer Sciencespecial edition podcast series provides members with direct access to the most clinically relevant and practice-informing advances in lung cancer, curated and interpreted by thoracic surgeons for thoracic surgeons.
This afternoon, the Centers for Medicare & Medicaid Services (CMS) released the Calendar Year (CY) 2027 Medicare Physician Fee Schedule (PFS) proposed rule. STS has put together a summary of key provisions affecting cardiothoracic surgery in the rule.
Physician Payment
As required by statute starting in CY 2026, there are two separate conversion factors (CFs): one for physicians and practitioners participating in qualifying alternative payment models (or QPs) and one for those who are not (non-QPs). For CY 2027, CMS has proposed a conversion factor (CF) of $32.84 for non-QPs and $33.16 for QPs.
While this is the second year in a row we are seeing base CF updates, as required by statute, the conversion factor for physicians will actually decrease due to the expiration of the temporary 2.5 percent increase for CY 2026, even though the formula incorporates positive base updates.
Additionally, other policies continue to diminish hospital-based proceduralists’ reimbursement. Policies such as the efficiency adjustment and reductions to practice expenses continue to threaten surgeons’ ability to practice. Reimbursement also continues to lag inflation. STS is working with the broader physician community and members of the Republican and Democratic Doctors Caucuses to reform physician reimbursement.
Surgical Global Codes
CMS continues to question the valuation of 10- and 90-day global surgical codes. While it does not make any proposal to conduct an across-the-board revaluation at this time, CMS states that it is interested in how “CMS could 'right-size' payments for the globals over time to ensure they remain aligned with current clinical practice and resource costs, are more readily updated based on empirical data, and do not obscure differences in cost and value across settings of care.” STS has consistently pushed back against efforts to reduce payments in surgical global periods, advocating for accurate valuation of surgical services and policies that reflect the complexity, intensity, and longitudinal care provided by cardiothoracic surgeons.
Quality Payment Program (QPP)
CMS is proposing to sunset the traditional Merit-based Incentive Payment System (MIPS) reporting option in 2029 and is pushing forward with its efforts to transition all MIPS participants towards MIPS Value Pathways (MVPs), which will be reported by subspecialty.
Inpatient Only (IPO) List in Hospital Outpatient Rule
CMS also recently released the CY 2027 Hospital Outpatient Prospective Payment System (OPPS) rule. Hospitals that meet their outpatient quality reporting requirements will receive a 2027 payment increase of 2.4%.
Additionally, CMS has long maintained an Inpatient Only (IPO) list identifying services that are not payable under the OPPS because they must be performed on an inpatient basis. In last year's rulemaking, CMS finalized the elimination of the IPO list over three years, suggesting it gives physicians greater flexibility in determining the most clinically appropriate site of care.
As codes are removed from the IPO list, CMS is pricing them for reimbursement in the hospital outpatient and Ambulatory Surgical Center (ASC) settings. Removal from the list does not mean that the procedures cannot be performed in the hospital inpatient setting, only that, if safe for the patient, they may now be performed in and paid for in the outpatient or ASC setting.
CY 2027 marks the second year of this transition. Of particular interest to STS members, CMS is proposing to remove services from the respiratory, mediastinum, diaphragm, digestive, lymphatic, and endocrine clinical families, which include virtually all of the general thoracic procedures. Removal from the IPO list does not require that surgeries for Medicare patients be performed in the outpatient setting.
However, STS continues to have significant concerns that removal of CT surgery from the IPO list could impact patient safety and result in other insurers dictating where surgeries are performed without proper safeguards or clinical input.
In this episode, co-hosts Dr. Sara Pereira and Dr. Ian Bostock celebrate the 20th anniversary and impact of the STS Looking to the Future (LTTF) Scholarship Program by speaking with three rising stars pursuing careers in cardiothoracic surgery: Tyler Wilson, MD, a general surgery resident at the University of Chicago; Molly Shields, MD, a general surgery resident at Walter Reed National Military Medical Center; and Tyrone Hill, a medical student at Meharry Medical College.
Earlier this month, the House Committee on Appropriations marked up its fiscal year (FY) 2027 appropriations bill for the Department of Health and Human Services (HHS). The House bill would provide $110.8 billion in discretionary funding for HHS, a reduction of $4 billion.